
Article: Understanding Melasma: Causes, Triggers and Modern In-Clinic Treatments

Understanding Melasma: Causes, Triggers and Modern In-Clinic Treatments
Melasma is a common pigmentation condition that causes flat, irregular patches of brown, grey-brown or occasionally blue-grey discolouration. It usually appears symmetrically on the cheeks, forehead, upper lip, nose and chin, although it can also affect the neck or forearms.
While melasma is harmless, its visibility and tendency to return can make it frustrating to manage. It is not caused by poor hygiene, and it cannot simply be scrubbed or exfoliated away. Successful treatment usually requires a long-term combination of daily sun protection, carefully selected skincare and, where appropriate, professionally administered treatments.
What causes melasma?
Melasma develops when melanocytes - the cells responsible for producing melanin - become overactive and create more pigment than the surrounding skin. There is rarely one isolated cause. Instead, several factors often overlap.
Hormonal changes
Melasma is strongly associated with hormonal activity. It commonly develops during pregnancy, when it is sometimes called the "mask of pregnancy", and may also be influenced by hormonal contraception or hormone replacement therapy. This does not mean that everyone experiencing hormonal changes will develop melasma; genetic susceptibility and light exposure also play important roles.
Anyone who suspects that medication is contributing to their pigmentation should speak to their doctor rather than stopping prescribed treatment independently.
Genetic predisposition
A family history of melasma increases the likelihood of developing it. The condition can affect every skin tone, but it is especially common in people whose skin naturally produces more melanin, including those of Asian, Middle Eastern, Latin American, Mediterranean and African heritage.
Sun and visible light
Ultraviolet radiation is one of the most significant melasma triggers. UVA penetrates deeply into the skin, while UVB contributes to surface damage and inflammation. Both can stimulate pigment production.
Visible light, particularly high-energy visible light from the sun, may also worsen pigmentation in susceptible skin. This is one reason tinted sunscreens containing pigments such as iron oxides are often recommended as part of a melasma-management plan.
Heat and inflammation
Heat may aggravate melasma in some people, even without direct sun exposure. Hot climates, saunas, steam rooms and intense heat-producing exercise can therefore contribute to flare-ups.
Inflammation is another concern. Harsh exfoliation, irritating active ingredients and poorly selected cosmetic procedures can disrupt the skin barrier and trigger post-inflammatory pigmentation, making the complexion appear more uneven.
Everyday triggers that can undermine treatment
Melasma often darkens during summer and fades somewhat in winter, but year-round management is essential. Common triggers include:
- Unprotected daylight exposure, including short walks, driving and sitting beside a bright window.
- Inadequate sunscreen application, such as applying too little or failing to reapply during prolonged exposure.
- Hormonal fluctuations, including pregnancy and certain hormonal medicines.
- Excessive heat, particularly when it repeatedly causes facial flushing.
- Skin irritation, whether from aggressive treatments, over-exfoliation or combining too many active products.
- Inconsistent treatment, especially stopping sun protection once pigmentation begins to improve.
Electronic screens are sometimes blamed for melasma. However, current evidence indicates that their visible-light output is far lower than sunlight and is unlikely to produce comparable pigmentary effects during normal use.
The role of daily skincare
Skincare cannot change genetic or hormonal susceptibility, but it can support treatment, limit aggravating factors and help maintain results.
Begin with consistent photoprotection
Daily broad-spectrum sunscreen is the foundation of melasma care. Choose SPF 30 or higher - ideally SPF 50+ - and apply it generously every morning. Reapply when spending extended periods outdoors, sweating or swimming, and combine it with shade and a broad-brimmed hat.

Within the REFORM Skincare range, options include SPF 50+ Antioxidant Sunscreen and SPF 50+ Tinted Sunscreen. A tinted formula may be particularly useful where visible-light protection is part of the treatment strategy. Sunscreen should still be reapplied as directed and used alongside sensible sun avoidance.
Introduce active ingredients carefully
Antioxidants such as vitamin C can complement sunscreen by helping defend the skin against oxidative stress and improving the appearance of uneven tone. REFORM Skincare Vitamin C 20% Serum or HYAL Vitamin C + E Serum may be considered within a morning routine, followed by moisturiser and sunscreen.
Retinoids support skin-cell turnover and can help improve uneven pigmentation over time. REFORM Skincare Retinol 1% Crème is a high-strength formula intended to address concerns including texture and dark spots. It should be introduced gradually, used at night and not applied during pregnancy. Those with sensitive skin, or anyone already using prescription treatment, should seek professional guidance before adding it.
Skin-barrier support is equally important. REFORM Skincare Vitamin B5 Gel can add hydration, while the Skin Barrier Repair Cream may help dry or compromised skin. If a product causes persistent burning, redness or peeling, stop using it and obtain advice. More irritation does not mean better results.
Modern in-clinic treatments
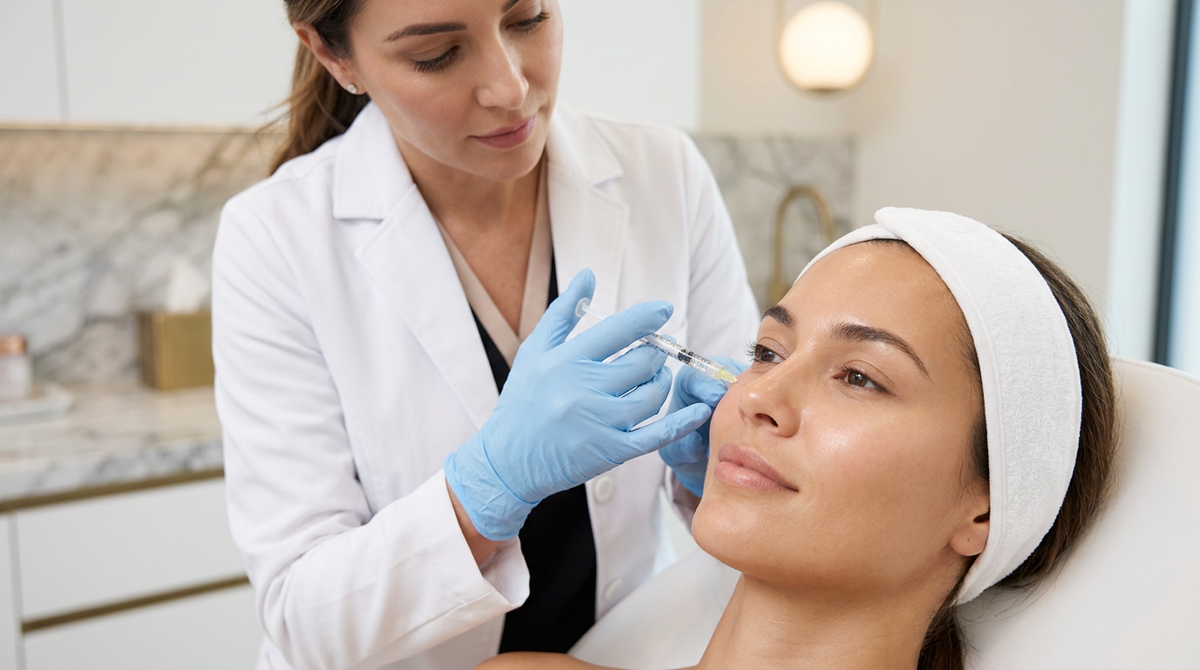
A professional assessment should come before any procedure. A dermatologist or suitably qualified clinician can confirm that the pigmentation is melasma, assess its depth and distinguish it from conditions such as post-inflammatory hyperpigmentation, lentigines or, more rarely, potentially serious skin changes.
Prescription topical treatment
Although applied at home, prescription therapy is often the clinical starting point. Depending on the patient, a clinician may recommend hydroquinone, azelaic acid, tretinoin, cysteamine, tranexamic acid or a short course of a triple-combination cream. These treatments require supervision because inappropriate or prolonged use can cause irritation or other complications.
Chemical peels
Superficial peels containing ingredients such as glycolic, lactic or salicylic acid can accelerate the removal of pigment-containing surface cells. They are generally used as an adjunct to topical treatment rather than a stand-alone cure.
Peel type and strength must be matched to the person's skin tone, sensitivity and pigmentation pattern. Aggressive peeling may cause inflammation and post-inflammatory hyperpigmentation, particularly in deeper skin tones. Superficial, carefully controlled treatments are usually favoured.
Microneedling
Microneedling creates controlled microchannels in the skin and may enhance the delivery of selected topical ingredients. Some clinicians combine it with tranexamic acid or other pigment-targeting treatments. Evidence is developing, but technique and patient selection matter: excessive treatment can aggravate inflammation rather than improve pigmentation.
Tranexamic acid treatments
Tranexamic acid may be used topically, delivered through procedures or, in selected cases, prescribed orally. Oral treatment is not suitable for everyone because it may increase the risk of blood clots. A detailed medical assessment is essential, particularly for anyone with clotting disorders, relevant family history or other risk factors.
Laser and light-based therapies
Low-fluence pigment lasers, picosecond devices, fractional lasers and intense pulsed light may be considered for carefully selected patients. These technologies can target pigment or promote skin renewal, but melasma does not always respond predictably.
Temporary improvement may be followed by recurrence, and excessive heat or energy can trigger inflammation and rebound pigmentation. Reviews of laser and light treatments continue to report risks including post-inflammatory colour changes, so these procedures should be undertaken only by clinicians experienced in treating melasma and diverse skin tones.
A long-term management strategy
Melasma is better understood as a controllable, relapsing condition than something permanently removed by a single treatment. A sensible plan usually follows three stages:
- Stabilise the skin with gentle cleansing, adequate hydration and rigorous daily sun protection.
- Reduce pigmentation gradually using appropriate active or prescription ingredients, with an in-clinic procedure added only when suitable.
- Maintain the improvement with continued photoprotection and a simpler long-term skincare routine.
The most effective approach is rarely the most aggressive one. Consistency, careful treatment selection and prevention of inflammation generally produce safer, more sustainable results than repeatedly trying to strip pigment from the skin.

Leave a comment
This site is protected by hCaptcha and the hCaptcha Privacy Policy and Terms of Service apply.